

- Difference Between Gastric Sleeve and Gastric Bypass
- How Do Gastric Sleeve and Gastric Bypass Work?
- Differences in Success Rate Between Gastric Sleeve and Bypass
- Gastric Bypass vs Sleeve Cost in 2026
- Gastric Sleeve vs Gastric Bypass Pros and Cons
- Recovery Differences between Gastric Sleeve and Gastric Bypass
- Which Is More Dangerous Gastric Sleeve or Gastric Bypass?
- Which One is Better: Gastric Sleeve or Gastric Bypass?
- Real Patient Before and After Photos: Gastric Sleeve vs Gastric Bypass
- Get Expert Guidance About Gastric Sleeve vs. Gastric Bypass
- FAQs About Gastric Sleeve vs Gastric Bypass
The main difference between gastric sleeve and gastric bypass surgery is that gastric sleeve permanently removes approximately 75–80% of the stomach and is irreversible, while gastric bypass creates a small stomach pouch and reroutes part of the small intestine without removing the stomach itself. Both procedures restrict food intake and influence appetite hormones, but gastric bypass also reduces nutrient absorption to some extent. Unlike gastric sleeve, gastric bypass can sometimes be reversed, although reversal is complex and rarely performed.
When you're comparing gastric sleeve vs gastric bypass, three numbers matter most: success rate (85–90% for sleeve, 90–95% for bypass at 5 years), excess weight loss at 10 years (60–70% for sleeve, 70–80% for bypass), and cost (3,500–5,500 for sleeve vs 4,500–6,500 for bypass in Turkey).
Both are the most performed bariatric surgeries in the world, and both work, but they suit different patients. Gastric sleeve is simpler, safer, and has a quicker recovery. Gastric bypass causes faster weight loss and better control of type-2 diabetes, but has higher risks and requires lifelong vitamin supplementation. This 2026 comparison from Turkey Luxury Clinics Experts walks through every difference so you can decide with your surgeon.
Difference Between Gastric Sleeve and Gastric Bypass
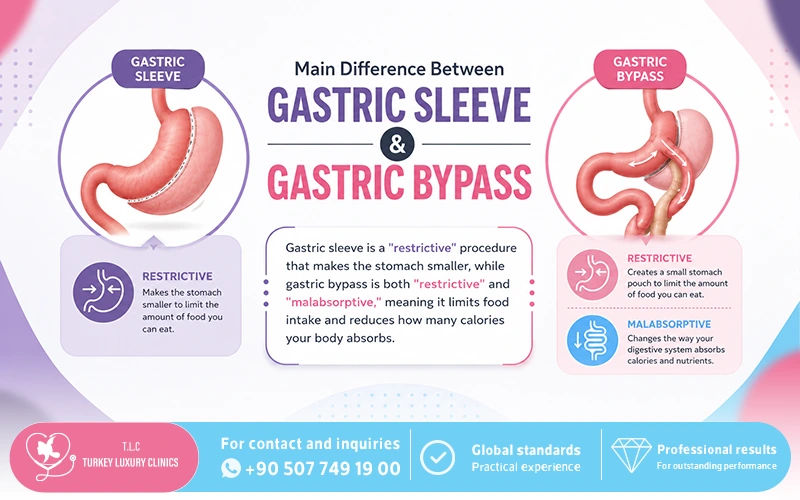
Gastric sleeve is a "restrictive" procedure that makes the stomach smaller, while gastric bypass is both "restrictive" and "malabsorptive," meaning it limits food intake and reduces how many calories your body absorbs.
Feature | Gastric Sleeve | Gastric Bypass (Roux-en-Y) |
How It Works | Removes approximately 75–80% of the stomach | Creates a small stomach pouch and reroutes the small intestine |
Appetite Effect | Reduces appetite through hormonal changes | Reduces appetite through hormonal and gut-related changes |
Total Weight Loss | 25–30% of total body weight | 25–35% of total body weight |
Weight Loss Success | Many patients achieve ≥50% excess weight loss | Many patients achieve ≥50% excess weight loss |
Safety | Generally lower short-term complication risk | Slightly higher short-term complication risk |
Surgery Duration | 45–90 minutes | 1.5–3 hours |
Hospital Stay | Typically 1–2 nights | Typically 1–3 nights |
Return to Work | Usually 2–4 weeks | Usually 2–4 weeks |
Excess Weight Loss (1 Year) | Approximately 60–70% | Approximately 65–80% |
Type 2 Diabetes Remission | Common; varies by patient and follow-up | Generally higher remission rates |
GERD (Acid Reflux) | May develop or worsen | Often improves existing GERD |
Reversibility | Irreversible | Technically reversible in selected cases, but rarely performed |
Long-Term Results | Sustained weight loss is possible, with some regain | Often slightly greater long-term weight loss maintenance |
The biggest difference between gastric sleeve and gastric bypass is how they change your digestive system. Gastric sleeve reduces stomach size while keeping the normal intestinal pathway, whereas gastric bypass creates a smaller stomach pouch and redirects food past part of the small intestine. Both procedures reduce food intake and influence appetite hormones, but bypass also changes nutrient absorption and produces additional metabolic effects.
These differences affect long-term outcomes. Gastric bypass generally produces slightly greater weight loss and often improves acid reflux and type 2 diabetes, but carries a higher risk of nutritional deficiencies and intestinal complications. Gastric sleeve is anatomically simpler and generally has fewer intestinal complications, although it may cause or worsen acid reflux. Both require lifelong nutritional follow-up and supplementation.
How Do Gastric Sleeve and Gastric Bypass Work?
Gastric Sleeve Mechanism
Gastric sleeve surgery, or Sleeve Gastrectomy, is a minimally invasive laparoscopic procedure that permanently removes approximately 80% of the stomach. The remaining portion is shaped into a narrow, tube-like "sleeve" about the size of a banana.
This procedure works through a dual mechanism:
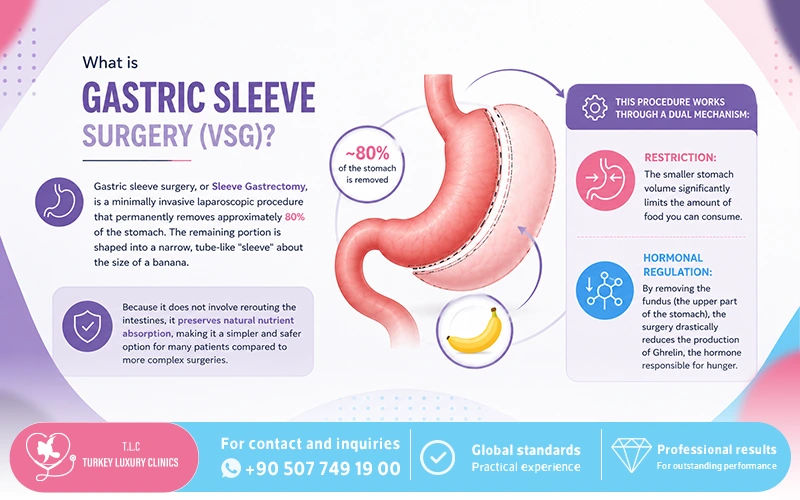
- Restriction: The smaller stomach volume significantly limits the amount of food you can consume.
- Hormonal Regulation: By removing the fundus (the upper part of the stomach), the surgery drastically reduces the production of Ghrelin, the hormone responsible for hunger.
Because it does not involve rerouting the intestines, it preserves natural nutrient absorption, making it a simpler and safer option for many patients compared to more complex surgeries.
Gastric Bypass (Roux-en-Y) Mechanism
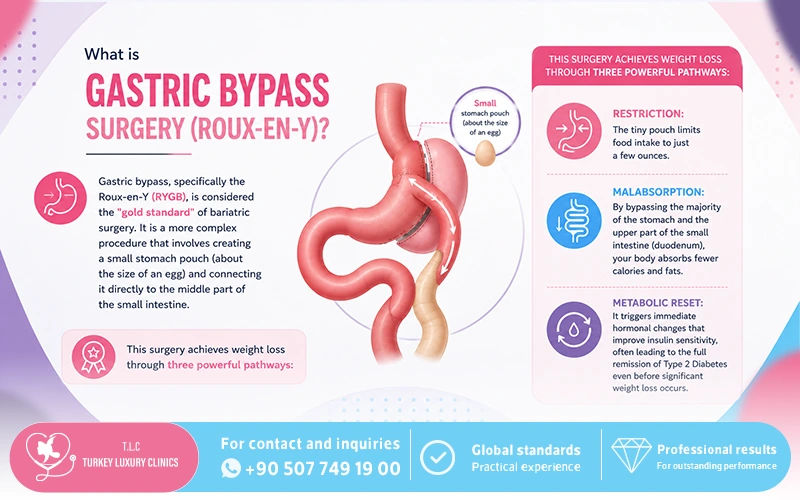
Gastric bypass, specifically the Roux-en-Y (RYGB), is considered the "gold standard" of bariatric surgery. It is a more complex procedure that involves creating a small stomach pouch (about the size of an egg) and connecting it directly to the middle part of the small intestine.
This surgery achieves weight loss through three powerful pathways:
- Restriction: The tiny pouch limits food intake to just a few ounces.
- Malabsorption: By bypassing the majority of the stomach and the upper part of the small intestine (duodenum), your body absorbs fewer calories and fats.
- Metabolic Reset: It triggers immediate hormonal changes that improve insulin sensitivity, often leading to the full remission of Type 2 Diabetes even before significant weight loss occurs.
Differences in Success Rate Between Gastric Sleeve and Bypass
Gastric sleeve has a success rate of 85–90% at five years, with patients losing and maintaining 55–65% of their excess body weight. Gastric bypass has a slightly higher success rate of 90–95%, with 60–70% excess weight loss maintained. Long-term success depends on lifelong adherence to diet, exercise, and medical follow-up.
Gastric Sleeve Success Rate (VSG)
Based on long-term clinical data, the Vertical Sleeve Gastrectomy shows reliable and consistent outcomes:
- 1 year: ~95% of patients lose 60–70% of excess body weight (EWL).
- 5 years: 85–90% of patients successfully maintain their weight loss.
- 10 years: 75–80% of patients remain above the 50% EWL threshold.
Gastric Bypass Success Rate (Roux-en-Y)
The Roux-en-Y Gastric Bypass remains the "gold standard" for rapid and sustained results:
- 1 year: ~97% of patients lose 70–80% of excess body weight (EWL).
- 5 years: 90–95% of patients maintain significant weight loss.
- 10 years: 80–85% of patients sustain results above 50% EWL.
Which Is More Successful for Weight Loss GS or GB?
In terms of weight loss alone, both procedures are considered highly successful. The difference is relatively small:
- Gastric bypass: slightly higher weight loss potential
- Gastric sleeve: slightly more consistent and technically simpler
Which Is More Successful for Metabolic and Health Improvements GS or GB
Gastric bypass usually leads to slightly more weight loss and better diabetes control than gastric sleeve. However, both procedures are highly effective in improving obesity-related conditions when combined with lifestyle changes.
- Both procedures improve conditions such as type 2 diabetes, hypertension, sleep apnea, and high cholesterol.
- Gastric Bypass tends to have a stronger and more immediate effect on blood sugar control, especially in insulin-dependent patients.
Factors That Affect Surgical Success Rates of GS and GB
While the procedure provides the tool, individual outcomes vary based on:
- Patient Compliance: Consistency with follow-up appointments and the 30/30 rule.
- Starting BMI: Patients with a BMI >50 may see different percentage results.
- Medical History: Pre-existing conditions like severe GERD or metabolic resistance.
- Age and Activity Level: Younger, more active patients often see faster metabolic resets.
Success Rate Over Years Between GS vs GB
Milestone | Gastric Sleeve (EWL) | Gastric Bypass (EWL) |
1 Year Post-Op | 60% – 70% | 70% – 80% |
5 Years Post-Op | 55% – 65% | 60% – 70% |
10 Years Post-Op | 50% – 60% | 60% – 75% |
Gastric Bypass vs Sleeve Cost in 2026
Procedure | Turkey Prices (All inclusive packages) | United States Prices (Without Insurance) |
Gastric Sleeve | $3,500 – $5,500 | $10,000 – $30,000+ |
Gastric Bypass | $4,500 – $6,500 | $18,000 – $35,000+ |
Gastric bypass generally costs more than gastric sleeve surgery because it's a more complex procedure, with sleeve costs often 20-25% less, though prices vary significantly by location, surgeon, hospital, and insurance, ranging from around $10,000-$30,000+ in the US without insurance, while bypass might be $18,000-$35,000+
In Turkey, gastric sleeve surgery costs $3,500–$5,500, while gastric bypass ranges from $4,500–$6,500.
Bypass surgery is generally more expensive due to the complexity of the procedure and longer operating time; however, both surgeries are significantly more affordable in Turkey than in Western countries.
Gastric Sleeve vs Gastric Bypass Pros and Cons
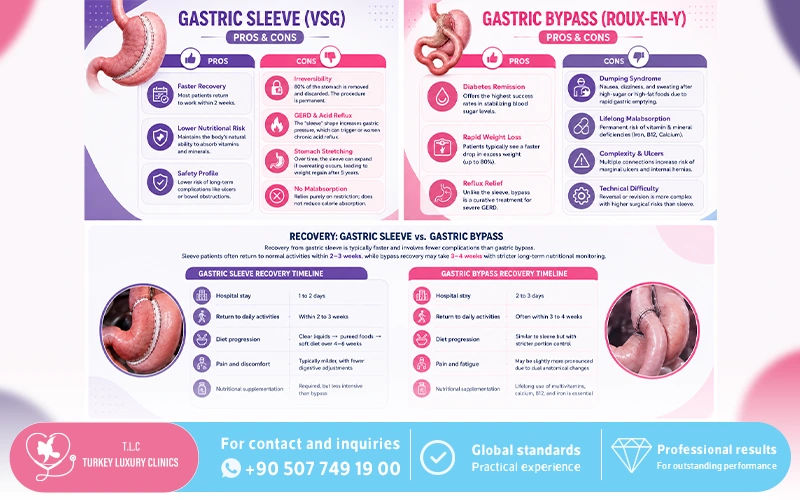
Pros of Gastric Sleeve
The Gastric Sleeve is favored for its surgical simplicity. By preserving the natural continuity of the digestive tract and avoiding intestinal rerouting, it offers:
- Faster Recovery: Most patients return to work within 2 weeks.
- Lower Nutritional Risk: It maintains the body’s natural ability to absorb vitamins and minerals.
- Safety Profile: A lower risk of long-term complications like ulcers or bowel obstructions.
Cons of Gastric Sleeve (VSG)
While the sleeve is simpler, it has specific anatomical and functional drawbacks:
- Irreversibility: Because 80% of the stomach is surgically removed and discarded, the procedure is permanent and cannot be reversed.
- GERD and Acid Reflux: The new "sleeve" shape increases internal gastric pressure, which can trigger or significantly worsen chronic acid reflux.
- Stomach Stretching: Over time, the sleeve can expand if the patient consistently overeats, which may lead to weight regain after the 5-year mark.
- No Malabsorption: Unlike the bypass, the sleeve relies purely on restriction; it does not help reduce calorie absorption.
Pros of Gastric Bypass
Often called the "Gold Standard," Gastric Bypass is a transformative procedure for those with severe obesity or metabolic issues. Its primary advantages include:
- Diabetes Remission: Offers the highest success rates in stabilizing blood sugar levels.
- Rapid Weight Loss: Patients typically see a faster drop in excess weight (up to 80%) compared to the sleeve.
- Reflux Relief: Unlike the sleeve, the bypass is a curative treatment for severe GERD.
Cons of Gastric Bypass (Roux-en-Y)
The bypass is more complex and introduces risks related to the rerouting of the digestive tract:
- Dumping Syndrome: Patients may experience nausea, dizziness, and sweating after consuming high-sugar or high-fat foods due to rapid gastric emptying.
- Lifelong Malabsorption: While this helps with weight loss, it also means a permanent risk of severe vitamin and mineral deficiencies (Iron, B12, Calcium).
- Complexity & Ulcers: The surgery involves multiple connections (anastomoses), which increases the risk of marginal ulcers and internal hernias.
- Technical Difficulty: If a reversal or revision is needed, the procedure is significantly more complex and carries higher surgical risks than sleeve revisions.
Recovery Differences between Gastric Sleeve and Gastric Bypass
Recovery from gastric sleeve is typically faster and involves fewer complications than gastric bypass. Sleeve patients often return to normal activities within 2–3 weeks, while bypass recovery may take 3–4 weeks with stricter long-term nutritional monitoring.
Gastric Sleeve Recovery Timeline
- Hospital stay: 1 to 2 days
- Return to daily activities: Within 2 to 3 weeks
- Diet progression: Clear liquids → pureed foods → soft diet over 4–6 weeks
- Pain and discomfort: Typically milder, with fewer digestive adjustments
- Nutritional supplementation: Required, but less intensive than bypass
Gastric Bypass Recovery Timeline
- Hospital stay: 2 to 3 days
- Return to daily activities: Often within 3 to 4 weeks
- Diet progression: Similar to sleeve but with stricter portion control
- Pain and fatigue: May be slightly more pronounced due to dual anatomical changes
- Nutritional supplementation: Lifelong use of multivitamins, calcium, B12, and iron is essential
Read more: How to Lose Weight 2 Years After Gastric Sleeve?
Which Is More Dangerous Gastric Sleeve or Gastric Bypass?
Gastric bypass is generally associated with a slightly higher risk of surgical and long-term complications than gastric sleeve, mainly because it involves rerouting the small intestine. However, both procedures have low mortality rates when performed in appropriately equipped hospitals by experienced bariatric surgeons.
Gastric bypass carries additional risks of internal hernias, marginal ulcers, dumping syndrome, and nutritional deficiencies. Gastric sleeve has a simpler surgical structure but is more likely to cause or worsen acid reflux (GERD), and some patients may eventually require conversion to gastric bypass.
The safest procedure depends on your medical history, existing reflux, nutritional status, and individual surgical risk factors.
Potential Risk or Side Effect | Gastric Sleeve | Gastric Bypass |
Acid reflux (GERD) | Higher risk of new or worsening reflux | Often improves existing reflux |
Dumping syndrome | Less common | More common |
Vitamin and mineral deficiencies | Possible; lifelong supplements required | Higher risk, particularly iron, B12, and calcium deficiencies |
Internal hernia | Not a typical procedure-specific complication | Recognized long-term risk |
Bowel obstruction | Possible but less common | Greater risk due to intestinal rerouting |
Marginal ulcers | Not applicable without a gastrojejunal connection | Recognized risk, especially with smoking or NSAID use |
Gastrointestinal leaks | Possible along the stomach staple line | Possible at surgical connections |
Bleeding and infection | Possible | Possible |
Strictures or narrowing | Can occur in the gastric sleeve | Can occur at the pouch–intestine connection |
Long-term reoperation or intervention | Generally lower likelihood | Generally higher likelihood |
Which Surgery Has a Lower Complication Risk?
Gastric sleeve generally has a more favorable short-term safety profile because it avoids intestinal rerouting. However, it may not be the safer long-term option for patients with severe gastroesophageal reflux disease (GERD).
Gastric bypass involves more complex intestinal reconstruction and requires careful lifelong nutritional monitoring, but it may offer important benefits for patients with significant acid reflux or poorly controlled type 2 diabetes.
The safest choice depends on your medical history, BMI, nutritional status, medications, and individual risk assessment by a qualified bariatric surgeon.
Which One is Better: Gastric Sleeve or Gastric Bypass?
Neither surgery is universally better than the other. In general, gastric sleeve is preferred for patients seeking a simpler operation, faster recovery, and lower long-term nutritional risks. In contrast, gastric bypass is often recommended for patients with severe GERD, poorly controlled type 2 diabetes, or very high BMI values. The right choice ultimately depends on your medical history, lifestyle habits, and weight-loss goals.
How to Choose?
Acid Reflux (GERD): If you suffer from severe, chronic heartburn or acid reflux, gastric bypass is usually the better choice. It significantly reduces reflux symptoms, whereas gastric sleeve may worsen or trigger GERD in some patients.
Type 2 Diabetes: Both surgeries improve diabetes, but gastric bypass generally produces stronger and faster metabolic improvements due to intestinal rerouting and hormonal changes.
Body Mass Index (BMI): Patients with a BMI above 50 often achieve better long-term weight loss with gastric bypass because it combines restriction with malabsorption.
Commitment to Vitamins: Gastric bypass requires strict lifelong vitamin and mineral supplementation. If long-term compliance is a concern, gastric sleeve may be easier to manage.
Medication Requirements: Patients who regularly use NSAID medications, such as ibuprofen, are often better candidates for gastric sleeve because NSAID use after gastric bypass increases the risk of ulcers.
Surgical Risk Tolerance: Gastric sleeve is technically simpler, preserves normal intestinal anatomy, and generally carries a lower risk of long-term nutritional complications.
Choose Gastric Sleeve if:
- You do not have severe GERD.
- You want a simpler procedure with faster recovery.
- You want to minimize long-term nutritional deficiencies.
- You regularly use NSAID medications.
Choose Gastric Bypass if:
- You have severe GERD or chronic acid reflux.
- You have poorly controlled type 2 diabetes.
- Your BMI is exceptionally high.
- You need maximum long-term weight loss and stronger metabolic benefits.
Real Patient Before and After Photos: Gastric Sleeve vs Gastric Bypass


Get Expert Guidance About Gastric Sleeve vs. Gastric Bypass

Still weighing your options? Whether you're leaning toward gastric sleeve or considering gastric bypass, making the right choice starts with trusted medical advice.
At Turkey Luxury Clinics, our bariatric experts provide free, personalized consultations to help you fully understand both procedures, from expected results to recovery and long-term care. Book your appointment with one of Turkey’s board-certified and internationally experienced bariatric surgeons today.
Related articles:
Gastric Sleeve Revision to Bypass: Best Option When Sleeve Fails
Can You Get a Gastric Sleeve Twice? Best Revision Options Turkey 2026
FAQs About Gastric Sleeve vs Gastric Bypass
















